


Breast Implants Sydney with a Specialist Plastic Surgeon
Breast implant surgery in Sydney is performed under general anaesthetic at an accredited private hospital, with a specialist anaesthetist providing care throughout. Most procedures take 60 to 90 minutes for a standard primary augmentation, with operative time extending where a lift is added or where revision work is required.
Implant selection is the single most discussed topic at consultation. Brand, surface, shape, size and profile all sit alongside the placement decision — subglandular, dual plane or submuscular — and none of those variables is independent of the others. Dr Turner works through each at consultation, with the surgical plan finalised after two consultations as required by the Medical Board of Australia.
For a broader view of what breast augmentation costs across Sydney practices, see the breast augmentation cost Sydney guide. Dr Turner’s own pricing is set out in full further down this page.
Understanding Breast Augmentation
Breast augmentation is a surgical procedure that uses implants, fat transfer, or a combination of both to alter breast size and shape. It is one of the most commonly performed cosmetic procedures in Australia, but the term covers a wide range of clinical situations — from a woman in her twenties whose breasts never developed to the size she would like, through to a patient in her forties addressing volume change after pregnancy.
What augmentation cannot do is correct significant sagging on its own. If the nipple sits below the breast crease, an implant alone will sit high on the chest while the tissue continues to hang below it, sometimes producing what surgeons call a double bubble. In those cases a breast lift with implants is likely to be the more appropriate plan. Dr Turner assesses this at consultation and will say directly which approach suits your anatomy.
Understanding Your Anatomy
Much of the confusion about implant size comes down to a misunderstanding of the underlying architecture. Breast tissue sits on top of the pectoralis major muscle, which sits on top of the rib cage. The implant is placed somewhere within that layered structure. How it looks afterwards depends as much on what is underneath as on what implant goes in.
Chest Wall Dimensions
The width and curvature of the rib cage place hard limits on what implant can fit. Two patients with identical breast volume can have very different chest wall shapes, and the same implant in those two patients will look quite different. Dr Turner takes detailed measurements of chest width, breast width, and the distance from the breast crease to the nipple before any implant size is discussed.
Breast Footprint
Your existing breast has a footprint — the area where it sits against the chest wall. Implants that match this footprint tend to give a more proportionate result. Implants that exceed the footprint, particularly in width, can produce visible edges, side fullness that looks unbalanced, and increased pressure on the tissues over time.
Tissue Quality and Coverage
Soft tissue thickness over the upper pole determines how much of the implant edge will be visible or palpable. Thin tissue means a higher chance of visible rippling, particularly with smooth round implants placed above the muscle. Thicker tissue allows more options. This is assessed with a pinch test at consultation.
Breast Augmentation Before and After Photos
View breast augmentation before and after photos from Dr Turner’s Sydney patients, including examples of round implants, anatomical implants, and results in patients with different body frames and breast shapes.
Before and after photos are examples only. Results vary between patients and depend on anatomy, tissue quality, implant choice, surgical plan and healing. No particular outcome can be assured.
View breast augmentation before and after photos
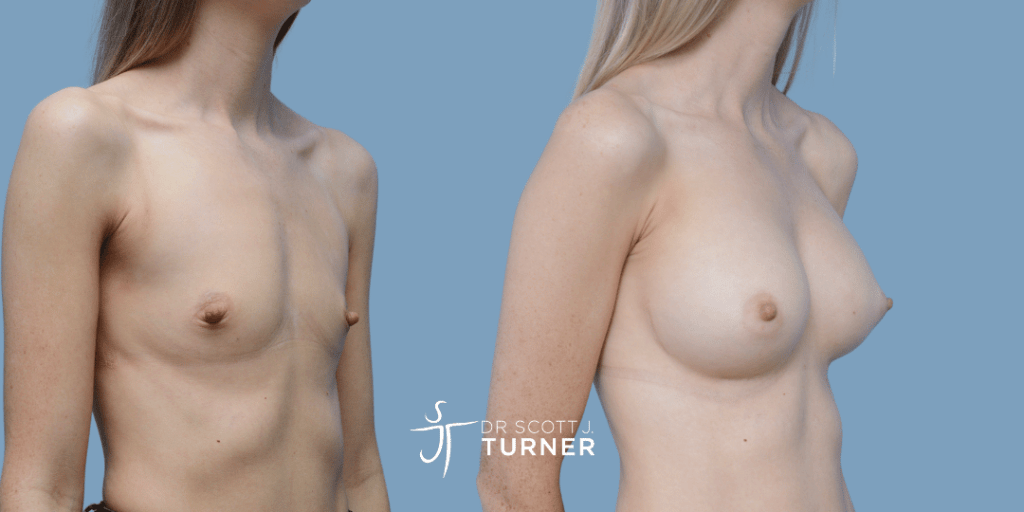
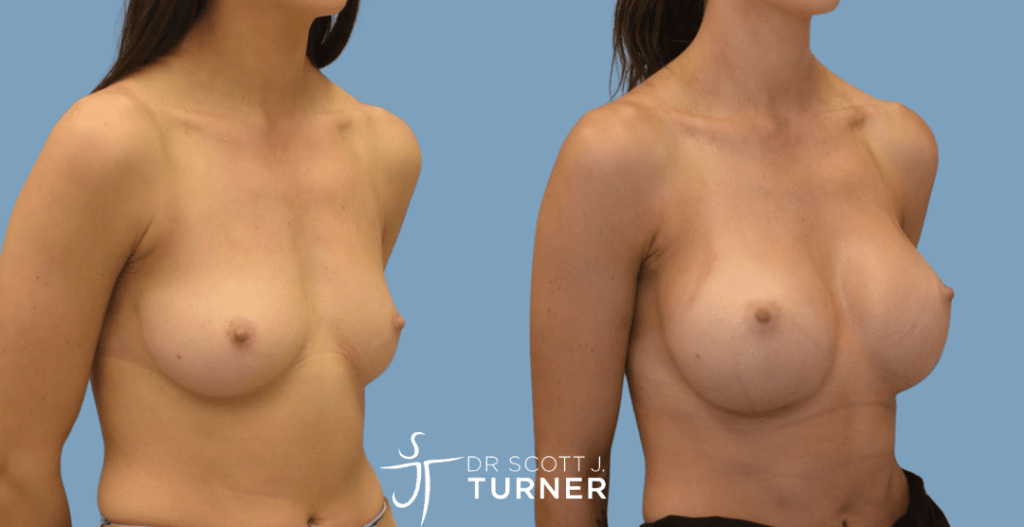
Round Breast Implants
Examples of round breast implants, the shape most commonly used in primary augmentation.
View round breast implant before and after photos
Teardrop Breast Implants
Examples of anatomical implant results in selected patients.
View teardrop breast implant before and after photos
Asian Breast Augmentation
Examples of breast augmentation in Asian patients, where tissue thickness and frame dimensions often differ from the population average and influence implant selection.
Dr Turner’s Approach: Tissue-Based Planning
Tissue-based planning means starting with what your anatomy can support, then working out which implant fits within those parameters. The alternative — still common in some practices — is to start with a desired cup size and force-fit an implant to achieve it.
The problem with the cup-size-first approach is that cup sizing is not standardised across bra manufacturers, and it tells the surgeon nothing about whether a given implant will fit the chest wall safely. Patients who request an implant width significantly beyond their breast footprint have higher rates of bottoming out, lateral implant displacement, and tissue thinning over time.
The aim is the largest implant that fits comfortably within the existing footprint and tissue coverage, with a profile suited to chest depth. That is typically the result that holds its shape longest.
How Do I Choose the Right Breast Implants?
There are five variables to work through with every implant decision: brand, size, shape, profile and surface texture. None is independent of the others, which is why the implant conversation takes up a substantial portion of the consultation.
Implant Brands
Breast implants in Sydney are regulated by the Therapeutic Goods Administration. Dr Turner uses TGA-approved implants from two manufacturers, both with established long-term safety records and both tracked through the Australian Breast Device Registry.
One has more than three decades of published clinical data behind it and offers cohesive silicone gel in both smooth and lightly textured surfaces. The other is a newer entrant that has gained international use over the last decade, using a softer gel, a smooth surface and an embedded microchip for traceability; it typically feels softer but requires careful handling during placement.
Neither is universally preferable. The right choice depends on your tissue characteristics, your preferences around feel and longevity, and the specifics of your case. Dr Turner will name and discuss both at consultation, alongside the manufacturer data for each.
Implant Size
Implant size is measured in cubic centimetres, not cup sizes. A 300cc implant in one patient may produce a different visual outcome than the same implant in another because of differences in chest wall, tissue coverage and existing breast volume.
In clinic, sterile sizers placed inside a sports bra give a more accurate sense of what a given volume will look like on your frame. This is more useful than trying implants in a fitting bra, which does not account for skin expansion or chest wall curvature.
Implant Shape: Round vs Anatomical (Teardrop)
Round implants are symmetrical, look the same from any angle, and cannot rotate out of position. Anatomical or teardrop implants have a profile shaped to follow the natural breast slope, fuller in the lower pole than the upper.
Round implants have become the default for most augmentation patients because cohesive gel technology means modern round implants no longer round out at the top in the way earlier generations did. They also tolerate small amounts of rotation without affecting the result. Anatomical implants can give a particular shape in the right candidate, but they must stay correctly oriented to look right, and rotation can cause asymmetry requiring revision.
In tuberous breast correction, anatomical implants often play a specific role because of the breast shape being corrected. For routine primary augmentation, round is more commonly used in current practice.
Implant Profile and Projection
Profile refers to how far the implant projects forward from the chest wall for a given base width. Implants come in low, moderate, moderate plus, high and extra high profile options.
Higher profile means more forward projection on a narrower base, which suits narrower chest walls where forward fullness is still wanted. Lower profile spreads the same volume over a wider base, which suits broader chests or a more spread appearance. Profile selection is one of the more nuanced parts of implant choice and is worked out during consultation rather than predetermined.
Implant Surface: Smooth vs Textured
Smooth implants have a polished outer shell. Textured implants have a roughened surface designed to grip surrounding tissue and reduce rotation in anatomical implants. Aggressive macrotextured implants, recalled internationally in 2019, were associated with the majority of BIA-ALCL cases reported globally.
Modern microtextured options carry a substantially lower BIA-ALCL signal than the recalled macrotextured products. Smooth implants have not been associated with BIA-ALCL. For most patients Dr Turner uses smooth implants. Textured options are considered where there is a specific clinical reason, such as preventing rotation in an anatomical implant.
Am I Suitable for Breast Augmentation?
Suitability is about more than wanting larger or differently shaped breasts. It depends on your anatomy, your physical health, your psychological readiness, and your understanding of what surgery can and cannot achieve.
Anatomical Considerations
You may be suitable if:
- Your breast development is complete (typically age 18 or older for cosmetic indications)
- You have adequate soft tissue coverage to support an implant
- Your nipple position sits at or above the breast crease, or your asymmetry is mild
- You have no significant ptosis (descent) requiring a lift
- Your chest wall has no severe asymmetry or deformity that would require reconstructive rather than cosmetic surgery
Where there is significant ptosis, a breast lift or a lift combined with implants is likely to be needed rather than augmentation alone. Dr Turner assesses this by physical examination at consultation.
Lifestyle and Health Factors
You will need to be:
- In good general health, with conditions such as diabetes well controlled
- At a stable weight, ideally near your long-term target weight
- A non-smoker, with smoking and vaping ceased for at least six weeks before and after surgery, as smoking substantially increases complication rates
- Free of active infection or wound healing conditions
- Realistic about what surgery can achieve and what it cannot
If you are planning future pregnancies, this is worth raising at consultation. Pregnancy and breastfeeding can change breast volume and tissue elasticity in ways that affect long-term results. There is no medical reason to wait, but some women prefer to defer surgery until their family is complete.
The Two-Consultation Process and Cooling-Off Period
Since the cosmetic surgery reforms came into effect in July 2023, every patient considering cosmetic breast augmentation must:
- Obtain a GP referral before the first consultation. Your GP provides a letter confirming your medical history, current medications, and any conditions that may affect surgery.
- Attend a minimum of two consultations with Dr Turner before surgery is booked. Dr Turner conducts these personally. There are no patient representatives or coordinators standing in for the surgeon.
- Be screened for psychological risk factors, including body dysmorphic disorder, with referral for formal assessment by a registered psychologist or psychiatrist where indicated. Patients under 18 require that assessment in every case.
- Observe a seven-day cooling-off period between giving informed consent and the date of surgery. Patients under 18 observe a three-month cooling-off period.
Some patients find these requirements frustrating, particularly after considering surgery for years. The intent is patient safety, and in practice the structured process tends to produce better-considered decisions.
How Is Breast Augmentation Surgery Performed?
Breast augmentation is performed under general anaesthetic in a fully accredited private hospital, with a specialist anaesthetist providing care throughout. The procedure typically takes 60 to 90 minutes for a standard primary augmentation, longer if a lift is added or revision work is involved.
Most patients are discharged the same day. An overnight stay is available and is often preferred by patients travelling from interstate, or by those who would rather have monitored first-night recovery.
Incision Options
Three incision options are used internationally for breast augmentation. Each carries trade-offs.
Inframammary Fold Incision
The inframammary fold incision sits in the natural crease beneath the breast. This is Dr Turner’s preferred approach for most primary augmentations. The scar is concealed in the crease and typically fades to a fine line within 12 to 18 months.
It allows precise pocket dissection, direct access for implant placement, and the use of any implant size or shape. Published capsular contracture rates are lower with this incision than with the periareolar approach. The trade-off is a scar in the breast crease, which for most women is acceptable because it is hidden in normal posture and clothing.
Periareolar Incision
The periareolar incision sits at the lower border of the areola, where pigmented skin meets breast skin. The scar can blend well into that colour transition, but the incision passes through breast tissue and milk ducts, which raises capsular contracture rates somewhat and may affect breastfeeding.
It is sometimes considered for patients also having a periareolar lift component, where the scar is being placed there in any case.
Trans-Axillary Incision, and Why It Is Not Offered
The trans-axillary incision is placed in the armpit. The advantage promoted for it is that no scar is left on the breast itself.
In practice the disadvantages are significant enough that Dr Turner does not use this approach. Pocket dissection is more difficult through a remote incision, which can affect implant positioning, and bleeding control is harder. The approach was developed for saline implants placed empty and filled in situ, which is not how modern silicone gel implants work. The armpit scar is also frequently visible in singlet tops and swimwear.
Implant Placement Options
Where the implant sits relative to the pectoralis major muscle is a separate decision from where the incision is placed. There are three options.
Subglandular (Above the Muscle)
The implant sits directly behind the breast tissue, above the pectoralis major. This may suit patients with adequate soft tissue coverage in the upper pole, and recovery is faster.
Trade-offs: greater visibility of implant edges in thin patients, higher capsular contracture rates, and more interference with mammographic imaging. Less commonly used in current practice for primary augmentation.
Submuscular (Under the Muscle)
The implant sits behind the pectoralis major. This provides additional soft tissue coverage in the upper pole and reduces visibility of implant edges, with lower capsular contracture rates.
Trade-offs: longer initial recovery because the muscle has been lifted, and animation deformity — visible movement of the implant when the pectoral muscle contracts — in some patients.
Dual Plane (Most Commonly Used)
Dual plane is a refinement of submuscular placement in which the upper portion of the implant sits beneath the muscle and the lower portion sits behind breast tissue alone. This combines the upper pole coverage of submuscular placement with the more natural lower pole behaviour of subglandular placement. For most primary augmentation patients, this is the placement Dr Turner recommends.
Placement is covered in more detail in the guide to implant placement over, under or dual plane.
Internal Support of the Lower Pole
Some augmentations are reinforced with an absorbable mesh or biological scaffold that provides additional internal support to the lower pole and lateral aspects of the breast — in effect a sling supporting the implant from inside, taking some of the long-term load off the skin envelope and the inframammary fold.
This may help reduce the rate of bottoming out, where the implant gradually descends below the natural breast crease over time; help maintain projection in patients with thin or stretched skin; and provide structural support in revision cases where tissue has thinned.
It adds a small amount to operative time and surgical complexity, and is not necessary for every primary augmentation. For patients with thin skin, weak inframammary fold support, or anatomy that would be difficult to support long-term with skin alone, it can make a meaningful difference to how well the result holds. Dr Turner discusses suitability case by case at the planning stage.
Hybrid Breast Augmentation and Fat Transfer
Hybrid breast augmentation combines an implant with fat transfer in the same procedure. The implant provides the underlying volume and projection. The transferred fat, harvested from another body area by liposuction, fills the upper pole, softens the implant edges, and addresses small contour irregularities or asymmetries.
The hybrid approach may suit patients with very thin tissue coverage, patients with mild upper pole hollowness, and those wanting a softer transition from chest wall to breast. It adds operative time and involves recovery in two body areas.
Fat transfer breast augmentation in Sydney is most often performed as this hybrid technique rather than on its own. Fat alone produces a modest and partly unpredictable volume increase, because a proportion of every graft is reabsorbed over the first few months — which is why fat-only augmentation rarely produces the result patients expect from a single procedure. Combining the two allows the implant to carry the volume while the graft does the refining work.
Breast fat transfer in Sydney carries a higher cost than implant-only augmentation, reflecting liposuction of the donor site, graft preparation and longer operative time. The indicative figure is set out in the cost section below. Not every patient is suitable: the donor area needs sufficient fat for harvest, and weight needs to be stable, since significant weight loss afterwards can reduce the volume of transferred fat.
Related Procedures
Where the nipple has descended below the inframammary fold, an implant alone will not raise it — a breast lift, or a breast lift with implants where volume has also been lost, is usually the more appropriate plan. Patients with a narrow breast base and constricted lower pole may require tuberous breast correction. Where existing implants are causing problems, see breast implant revision and removal.
Dr Turner’s 12-Point Surgical Protocol
What happens in the operating theatre matters as much as what was planned in the consultation room. The following protocol is followed for every primary breast augmentation Dr Turner performs.
- Pre-operative antibiotic prophylaxis administered intravenously by the anaesthetist
- Antiseptic skin preparation with chlorhexidine, with full draping of the operative field
- Precise marking of incision lines, breast crease and asymmetry adjustments while the patient is awake and standing, before anaesthesia
- Inframammary fold incision at the planned location, with careful dermal closure planning
- Pocket dissection under direct vision with diathermy haemostasis, avoiding blunt dissection beyond what is needed for implant placement
- Triple antibiotic pocket irrigation, following the internationally published plan for capsular contracture prevention
- Glove change and re-prep before implant handling, to reduce bacterial contamination of the implant surface
- No-touch insertion using a sterile funnel device, reducing surface contamination during placement
- Implant orientation check with the patient briefly tilted upright to assess symmetry before final closure
- Layered closure with absorbable sutures in deep dermis and subcuticular layers, with no external sutures requiring removal
- Surgical bra applied in theatre before the patient wakes
- Documentation in the Australian Breast Device Registry for long-term tracking, with implant batch numbers recorded
Other surgeons follow similar protocols and some vary in their approach. What is worth looking for is consistency — a surgeon who can articulate exactly what they do at each stage and why.
Recovery and Aftercare
Recovery is the part patients tend to underestimate. The surgery itself takes around 90 minutes. Recovery is a phased process running across several months.
First Week
The first 48 to 72 hours are the most uncomfortable, with tightness across the chest, particularly after submuscular or dual plane placement. Pain is typically managed with prescribed analgesia for the first four to five days, then over-the-counter medication.
You will need someone at home with you for at least the first 24 hours. No driving for at least a week, and longer while taking opioid analgesia. Sleeping on your back with your head elevated on two or three pillows is recommended for the first two weeks.
A surgical bra is worn continuously from theatre, removed only briefly for showering after day three.
Weeks 2 to 6
Most patients return to office-based work after 7 to 10 days. Lifting over 5kg, upper body exercise, and any activity engaging the pectoral muscle is restricted for six weeks.
Swelling subsides progressively over this period, though final settling takes longer. The implant typically sits high on the chest for the first two to three weeks before beginning to drop into position. This is expected.
Drop and Fluff: How Implants Settle
Drop and fluff describes how implants move from their initial high position into their final settled position over the first three to six months. The drop refers to vertical settling as the lower pole skin and pectoral muscle relax. The fluff refers to softening of the implant pocket and the transition from a tight, high look to a softer, more rounded final shape.
If your breasts look high and tight at week two, this is expected rather than a cause for concern. Most settling is complete by three months, with final shape settling at around six months.
Scar Management
Scars on the breast typically take 12 to 18 months to mature. During that period:
- Silicone scar therapy, gel or sheet, starting at three weeks post-operatively
- Sun protection over the scar for 12 months, as UV exposure causes hyperpigmentation
- Massage techniques as instructed at follow-up
- Laser scar treatment where scars become hypertrophic
Return to Work and Exercise
Most patients with office-based work return at 7 to 10 days. Physically demanding roles involving lifting, overhead reaching or chest engagement need four to six weeks before a return to full duties.
Light walking is encouraged from day one. Lower body strength training can resume at three to four weeks. Upper body and chest work waits until six to eight weeks, as does high-impact running and jumping, with appropriate sports bra support.
Follow-up appointments are scheduled at one week, one month, three months, six months and one year, all in person at the Sydney clinic. The full timeline is covered in the recovery after breast augmentation guide.
Risks and Complications
Every surgical procedure carries risk. The risks of breast augmentation are real and need to be understood before any decision is made.
General Surgical Risks
These apply to any surgery performed under general anaesthetic:
- Adverse reaction to anaesthetic agents
- Infection at the incision site
- Bleeding or haematoma formation
- Wound healing problems
- Deep vein thrombosis, uncommon with appropriate prevention
Procedure-Specific Risks
- Capsular contracture — scar tissue around the implant tightens, causing firmness, distortion and sometimes pain. Reported rates with modern technique are in the order of 5 per cent over 10 years.
- Implant malposition — the implant settles in the wrong position, and may require revision surgery.
- Bottoming out — the implant gradually descends below the breast crease over time.
- Rippling — visible or palpable folds in the implant, more common in thin patients with smooth round implants placed above the muscle.
- Changes in nipple sensation — reported in roughly 10 to 15 per cent of patients. Most resolves within 12 months; permanent change occurs in a minority.
- Implant rupture — silicone implants can rupture from trauma or over time. Modern cohesive gel means leakage is generally contained within the capsule rather than dispersing.
- Asymmetry — some natural asymmetry typically remains. Significant asymmetry is uncommon but can occur.
- Need for revision surgery — published series report around 20 per cent of augmentation patients undergoing revision within 10 years, for a range of reasons.
How Dr Turner Reduces Risk
Risk reduction is built into the surgical protocol above. Specifically:
- Triple antibiotic pocket irrigation to reduce capsular contracture rates
- No-touch funnel placement to reduce bacterial contamination of the implant surface
- Smooth implants used preferentially, based on long-term safety data
- Screening for risk factors before surgery, including smoking cessation, weight stability and control of medical conditions
- Australian Breast Device Registry registration, providing traceability if a future safety signal emerges with a specific implant model
No surgeon can eliminate risk. What can be done is to apply each evidence-based step that reduces it.
Breast Augmentation Cost in Sydney
Breast augmentation cost in Sydney depends on the type of procedure performed and whether additional techniques are needed to achieve a stable result suited to your anatomy and goals. A straightforward implant-only augmentation is usually less complex than a hybrid procedure with fat transfer, correction of asymmetry or tuberous features, or augmentation combined with a lift.
As a general guide:
Standard breast augmentation with implants — from $11,000 all-inclusive. This covers straightforward implant-only augmentation using TGA-approved implants, general anaesthetic, private hospital theatre time and routine follow-up care. It suits patients with good skin quality, adequate breast tissue and no significant descent, who want to add volume with implants alone.
Hybrid breast augmentation with implants and fat transfer — from $15,000 all-inclusive. This combines implants with fat transfer, usually harvested from the abdomen, flanks or thighs. The higher figure reflects the additional operating time and the fact that surgery is performed in both the breast and the donor areas.
Factors that may affect the total include implant choice, whether fat transfer is added, whether internal lower pole support is recommended, the degree of asymmetry or tuberous correction required, and the total operating time needed for your surgical plan.
Breast augmentation is usually a cosmetic procedure and is not eligible for Medicare rebates or private health insurance benefits. Limited rebates may apply only in specific reconstructive or recognised developmental conditions, such as reconstruction following mastectomy, or selected congenital breast conditions meeting Medicare criteria.
These figures are the all-inclusive cost of breast augmentation in Sydney and are not a quote. What you pay depends on the surgical plan agreed at your second consultation, and you will receive a personalised written quote covering surgeon, anaesthetist, hospital, implant and follow-up costs before you decide whether to proceed.
Frequently Asked Questions
How long does breast augmentation surgery take?
Primary breast augmentation typically takes 60 to 90 minutes in the operating theatre. Procedures involving fat transfer, hybrid augmentation or a lift component take longer. Full theatre time, including anaesthesia and emergence, is usually around two hours.
What is the 45-55 rule for breasts?
The 45-55 rule describes the proportion generally considered balanced in a breast: roughly 45 per cent of volume sitting above the nipple and 55 per cent below it, with the nipple angled slightly upward. It is a planning reference rather than a target every patient should be measured against. Dr Turner uses it alongside breast width, chest wall shape and tissue quality when selecting implant dimensions, since the same implant produces a different proportion on a different frame.
What age can I have breast implants?
Breast development needs to be complete, which for most women is the late teens or early twenties. Operating before then risks planning around a breast that will still change. Patients under 18 seeking cosmetic surgery face additional requirements, including a three-month cooling-off period and mandatory assessment by a registered psychologist or psychiatrist. There is no upper age limit; general health and anaesthetic fitness matter more than age itself.
Will I be able to breastfeed after breast augmentation?
Most patients retain the ability to breastfeed. The inframammary fold incision avoids breast tissue and milk ducts, which is one reason it is preferred over the periareolar approach in patients planning future pregnancies. No surgical approach can assure preservation of breastfeeding capacity, and some patients do experience reduced supply afterwards.
How long do breast implants last?
Modern silicone implants have no fixed expiry date. The historical ten-year replacement rule has been replaced by monitoring-based recommendations: regular review with your surgeon, MRI or ultrasound surveillance from five to six years onwards, and replacement only when clinically indicated. Many patients keep the same implants for 15 to 20 years or longer. See the implant lifespan guide for detail.
When can I return to work and exercise?
Most office-based patients return to work at 7 to 10 days, and physically demanding roles at four to six weeks. Light walking starts from day one, lower body training at three to four weeks, and upper body, chest work and high-impact activity at six to eight weeks.
Will breast augmentation affect mammograms?
Implants do affect mammographic imaging. Standard mammograms still work, but additional displacement views are needed to image breast tissue around the implant. Telling your imaging provider that you have implants is essential. For high-risk screening, MRI may be more useful than mammography alone.
Is breast augmentation covered by Medicare?
Cosmetic breast augmentation is not covered by Medicare. Limited circumstances exist where item numbers may apply, primarily reconstruction following mastectomy, or specific congenital conditions such as tuberous breast deformity in some cases. Standard cosmetic augmentation is paid privately.


